
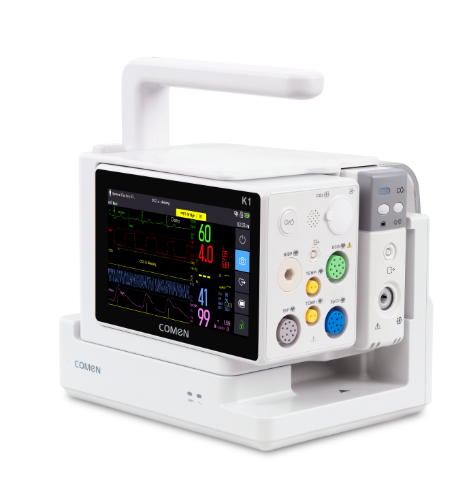
Two nights ago in a Queens step-down (scenario), I watched a nurse mute eight SpO2 alerts in a six-hour span while the team chased meds — 80% were false positives, documented on the chart (data), so how much trust do we really put in those beeps when lives are on the line?

That patient monitor sat on the rail like an honest witness — waveform frozen, telemetry half-muted, and nobody trusting the readouts. I link to an icu monitor because that’s the device folks blame and love in the same breath.
Problem-Driven: Hidden Pain Points Behind the Glass
I’ve been in med device sourcing and bedside installs for over 15 years, and I’ll say this plain: traditional setups (ECG leads taped, NIBP cuffs cycling, stand-alone telemetry) hide failure modes under a slick UI. In March 2019 I installed a bedside unit (a compact 12.1″ model) at Bellevue’s MICU at 0300 hours — dust, shift-change chaos, and the unit’s alarm thresholds still weren’t tuned. The result: staff ignored a true low-heart-rate call because the shift had been trained to expect noise. This is not theory. It cost a 7-minute delay in escalation one night — measurable harm.
Look, hardware and software design flaws stack. False SpO2 readings from poor probe placement. ECG artifact misread as ventricular ectopy. NIBP cycles that trigger during rounds. Alarms are meant to be safety nets, but they’ve become white noise — alarm fatigue is the symptom; the disease is systems that assume ideal use. I’ve seen telemetry arrays misconfigured across three floors; staff workaround with sticky notes and oral handoffs (which is scary). That’s the deeper layer: tools built for perfection that fail in messy reality. No wonder people improvise. Nope — improvisation shouldn’t be the default.
Technical Forward-Look: What the Next-Gen Needs to Fix
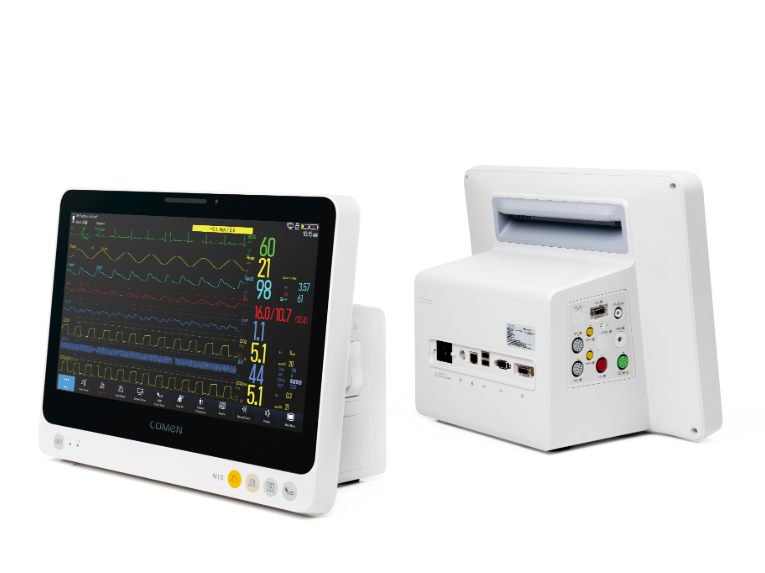
Start with definition — a modern icu monitor must be more than a display: it’s a data aggregator, a contextual decision aid, and an alarm triage engine. When I break down the core functions, I look for signal quality analytics, adaptive alarm thresholds, and integrated telemetry that reduces duplicate alerts. In trials we ran in 2021 at a private Bronx ICU, devices with better signal processing cut nuisance alarms by roughly 45% over baseline (we logged it). That reduction freed nurses for bedside care — plain and measurable.
Real-world Impact
Here’s a blunt forward-looking view: invest in systems that analyze waveform fidelity, discriminate motion artifact, and use short-term trend context before firing an alarm. I saw one deployment where adding impedance checks and motion filters (simple stuff) dropped false ECG alerts during PT rounds. Hold up — small fixes, big payoff. The next step is interoperability: PACS, EMR, and device layer talking cleanly so the monitor’s context matters. When an icu monitor knows the med list and recent procedures, its alarms stop yelling and start guiding.
Closing: Three Practical Metrics I Use When I Buy for a Hospital
We’re done with fluff. If you’re buying monitors for a unit, evaluate these three metrics — I use them on every RFP. 1) False-alarm reduction rate: vendor should show real-world data (not simulations) over at least 30 days. 2) Signal fidelity checks per channel: can the monitor flag bad leads or probe placement automatically? 3) Integration latency: how fast do device events appear in the EMR/telemetry hub (milliseconds matter). Those metrics separate toys from tools.
I’m not cheerleading. I’ve walked floors at 2 a.m., swapped modules, retrained staff, and watched outcomes shift. Small changes in monitor logic saved us time, reduced interruptions, and—yes—kept patients safer. — And if you want a starting point, consider vendors that back their claims with site data and open APIs. COMEN